October 2026 - The Clinical Edge
Medical Malpractice, Anesthesia Safety, Local Anesthetic Systemic Toxicity
Understanding LAST (Local Anesthetic Systemic Toxicity): A Guide for Legal Teams
Local Anesthetic Systemic Toxicity (LAST) is rare but potentially devastating. For attorneys on either side of a malpractice claim, recognizing what it is, who is at risk, and how it appears in the chart is essential to evaluating liability and causation.
Local Anesthetic Systemic Toxicity in Focus
What legal teams must know about risk, recognition, and records
What Is Local Anesthetic Systemic Toxicity (LAST)?
Local anesthetics are commonly used to numb a specific area of the body for procedures ranging from dental work to major surgery. Local Anesthetic Systemic Toxicity (LAST) occurs when too much of that drug enters the bloodstream, affecting the central nervous system and cardiovascular system throughout the body rather than staying confined to the intended site of action.
Clinically, LAST often begins with neurologic symptoms such as tinnitus, metallic taste, confusion, agitation, or seizures. If the exposure is large or not recognized promptly, it can progress to serious cardiovascular complications, including arrhythmias, hypotension, and cardiac arrest. The onset may be rapid (within minutes of injection) or delayed, especially with continuous infusions or high-volume blocks.
For legal purposes, two questions usually dominate: Was the use of the local anesthetic within the standard of care? and Was LAST recognized and treated appropriately and in time? The answers typically live in the medical record details—dose calculations, monitoring notes, and response to early warning signs.
Key Risk Factors for LAST
LAST is uncommon, but not random. Certain patient, drug, and procedural factors significantly increase risk. Understanding these helps legal teams assess whether clinicians appropriately anticipated and mitigated danger.
High total dose or concentration: Exceeding recommended milligrams per kilogram, using more concentrated solutions, or combining multiple local anesthetics can push plasma levels into toxic ranges.
Intravascular or near-vascular injection: Accidental injection directly into a blood vessel, or very close to one, can cause a sudden spike in systemic levels, often with rapid-onset symptoms.
Extremes of age: Infants, small children, and elderly patients generally tolerate lower doses and may require more conservative dosing and closer monitoring.
Low body weight or frailty: Underweight or cachectic patients are more vulnerable to “standard” doses that are not properly weight-adjusted.
Pre‑existing cardiac, hepatic, or renal disease: Impaired metabolism or reduced cardiac reserve lowers the margin of safety and can worsen outcomes if toxicity occurs.
Use of potent, longer‑acting agents: Drugs such as bupivacaine and ropivacaine carry a higher risk of severe, prolonged cardiovascular toxicity than some shorter‑acting alternatives.
Inadequate monitoring or resuscitation readiness: Performing high‑dose regional blocks without continuous monitoring or immediate access to intralipid (lipid emulsion therapy) can turn a manageable event into a catastrophe.
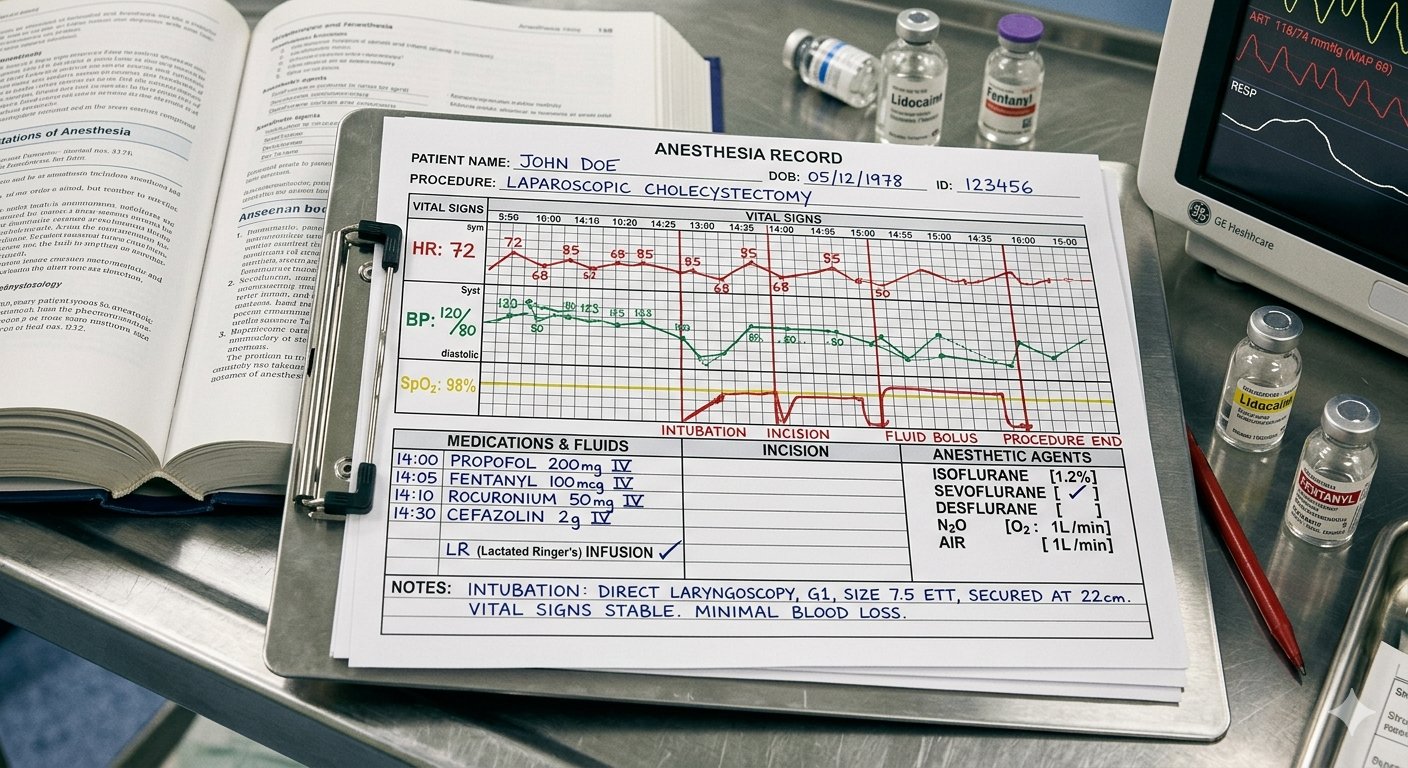
Detailed anesthesia records often reveal whether LAST risk was anticipated, monitored, and managed.
What the Defense Should Look for in the Medical Records
Defense counsel aims to demonstrate that clinicians acted within the standard of care and responded appropriately once problems emerged. The following documentation points can be critical in building that argument:
Weight‑based dosing and calculations: Clear notation of the patient’s weight, the drug used, concentration, total dose, and how it was calculated. Consistency with accepted dosing guidelines strongly supports appropriate planning.
Technique and precautions: Documentation of aspiration before injection, use of incremental dosing, ultrasound guidance for nerve blocks, and avoidance of known high‑risk sites can all indicate careful technique aimed at minimizing intravascular injection.
Monitoring records: Continuous blood pressure, heart rate, oxygen saturation, and rhythm strips before, during, and after administration show vigilance. Timed entries that correlate symptom onset with vital sign changes help reconstruct events accurately.
Recognition and response timeline: Notes reflecting early recognition of neurologic signs (e.g., agitation, seizure), prompt initiation of airway support, benzodiazepines, lipid emulsion therapy, and advanced cardiac life support (if needed) suggest an appropriate, timely response to suspected LAST.
Availability and use of intralipid: Records that confirm lipid emulsion was immediately available in the procedure area, along with dosing, timing, and response, are especially persuasive because lipid therapy is a widely recognized cornerstone of LAST treatment.
Informed consent and risk discussion: A consent form or note documenting discussion of anesthesia options and potential complications, including systemic reactions, can help establish that the patient was appropriately informed of rare but serious risks.
📌 Key Takeaway for Defense: A well‑documented, guideline‑consistent approach to dosing, monitoring, and rapid treatment of adverse signs can strongly support that the care team met the standard of care, even when LAST occurred.
What the Plaintiff Should Look for in the Medical Records
Plaintiff attorneys, by contrast, are often trying to show that LAST was preventable or that a delayed or inadequate response worsened the outcome. Gaps, inconsistencies, and omissions in the chart can be as revealing as what is documented clearly.
Unclear or excessive dosing: Missing weight, absent dose calculations, or totals that exceed recommended limits for the drug and patient type may suggest unsafe practice. Look for conflicting entries between the anesthesia record, nursing notes, and pharmacy documentation.
Lack of technique detail: Vague entries such as “block performed” without mention of aspiration, incremental injection, or ultrasound use may support an argument that safety steps were not followed or not prioritized, especially in high‑risk blocks.
Inadequate monitoring: Long gaps in vital signs, missing rhythm strips, or sparse documentation around the time of injection can raise questions about vigilance. Sudden deterioration without preceding recorded data may suggest that changes went unnoticed or unrecorded.
Delayed recognition and treatment: Compare the time of drug administration, first neurologic or cardiovascular symptoms, and initiation of interventions. A long delay before airway support, seizure control, or lipid therapy can be central to arguing that the standard of care was not met and that earlier action might have changed the outcome.
Absence or unavailability of intralipid: If there is no record of lipid emulsion in the crash cart, no order placed, or a significant delay in obtaining it, this can be a powerful point, given current expectations for facilities performing high‑dose regional anesthesia or blocks with potent agents.
Documentation inconsistencies and late entries: Note any post‑event addenda, altered times, or discrepancies between physician, nurse, and paramedic or transfer records. These may suggest attempts to reconcile or retroactively justify the timeline of events after a poor outcome.
💡 Pro Tip for Plaintiffs: Build a minute‑by‑minute reconstruction of the procedure and collapse, aligning medication times, nursing notes, anesthesia records, and emergency responses to highlight delays or missed warning signs.
Bringing It Together: Using LAST to Evaluate a Case
LAST sits at the intersection of pharmacology, procedure technique, and crisis management. For legal teams, it is not enough to know that a local anesthetic was given and a collapse followed. The strength of a case—defense or plaintiff—often depends on the fine print: dose calculations, risk assessment, monitoring vigilance, and the speed and completeness of the response once toxicity was suspected or should reasonably have been recognized.
References:
Guidelines for care of the patient receiving local-only-anesthesia. In:Guidelines for Perioperative Practice. AORN Inc; 2026. https://doi.org/10.6015/q617c8
Neal JM, Barrington MJ, Fettiplace MR, et al. The Third American Society of Regional Anesthesia and Pain Medicine Practice Advisory on Local Anesthetic Systemic Toxicity: Executive Summary 2017. Reg Anesth Pain Med. 2018;43(2):113-123. https://doi.org/10.1097/AAP.0000000000000720.
Checklist for Treatment of Local Anesthetic Systemic Toxicity (LAST):https://asra.com/news-publications/asra-updates/blog-landing/guidelines/2020/11/01/checklist-for-treatment-of-local-anesthetic-systemic-toxicity
Successful Local Anesthetic Systemic Toxicity (LAST) Management...:https://pmc.ncbi.nlm.nih.gov/articles/PMC12234403/
Local Anesthetic Toxicity:https://www.ncbi.nlm.nih.gov/books/NBK499964/
Silver State Legal Nurse Consulting bridges the gap between complex anesthesia care and clear legal strategy in suspected LAST cases. Our nurses with anesthesia and critical-care experience can: assemble anesthesia records, nursing flowsheets, medication administration records, and code summaries into a coherent, chronological timeline of even. We calculate weight‑based doses, identify high‑risk drugs and techniques, and flag patient comorbidities that may have increased vulnerability to LAST. We compare the documented monitoring, recognition of early signs, and timing of interventions (including lipid therapy) to current standards and guidelines. For both plaintiff and defense teams, we help identify strengths, weaknesses, and key issues for expert review, deposition, and trial.
📌 How We Add Value: By translating dense clinical data into clear, case‑focused insights, Silver State Legal Nurse Consulting helps attorneys quickly determine whether a suspected LAST event supports filing, defending, or resolving a claim.
Send us an email:
Give us a call or text:
(702) 482-9769


